19751 E Smoky Hill Rd #A, Centennial, CO 80015


Breastfeeding pain and a poor latch often happen when a baby cannot take enough breast tissue into their mouth. Positioning, breast fullness, and an infant’s oral movement can all play a role.
A tongue-tie may contribute to feeding difficulties, but it is not the cause of every painful latch. A lactation specialist and your baby’s pediatrician can assess feeding and weight gain. If restricted tongue movement is suspected, 303 Pediatric Dentistry in Centennial can evaluate your baby’s oral anatomy and discuss whether treatment is appropriate.
Breastfeeding can take practice for both parent and baby, especially in the first days after birth. Brief tenderness when a baby first latches may occur, but pain that continues throughout a feeding, cracked nipples, or a baby who repeatedly slips off the breast deserves attention. You do not need to wait for the problem to become severe before asking for help. Persistent pain can make feeding stressful and may be a sign that your baby is having trouble removing milk effectively.
One common cause is a shallow latch. Instead of taking a generous amount of breast tissue into their mouth, a baby may grasp mainly the nipple. That concentrates pressure on sensitive tissue and can leave the nipple sore or misshapen after feeding. Positioning can make a difference: bringing your baby close, allowing them to open their mouth wide, and helping them latch deeply may improve comfort. If a latch hurts beyond the first moments, a lactation specialist can watch a feeding and help you adjust it.
Breast fullness can also make it harder for a newborn to latch. When the area around the nipple is firm, your baby may struggle to get enough tissue into their mouth. Breast or nipple pain can have other causes, too. If pain persists despite positioning changes, or you have significant cracking, breast redness, or fever, contact your own healthcare professional for an assessment.
A tongue-tie occurs when the tissue beneath the tongue restricts its movement. Some babies with restricted movement have difficulty maintaining a latch or transferring milk. Parents may notice clicking sounds, frequent unlatching, long or frustrating feeds, or nipple pain. These signs are reasons to assess feeding, but they do not prove that a tongue-tie is present or that it is the source of the problem.
At 303 Pediatric Dentistry, we evaluate concerns about lip and tongue ties and offer pediatric frenectomies when appropriate. An assessment considers how your baby’s mouth functions, not simply how a band of tissue looks. Feeding support and an evaluation of other possible causes are important before deciding whether a procedure is needed. For some infants with a significant restriction and ongoing problems, a frenectomy may help reduce nipple pain, but no procedure can guarantee a comfortable latch.
A painful latch does not always mean your baby is getting too little milk, but intake should be checked when feeding is difficult. Your baby’s pediatrician can review weight changes and growth. Wet and dirty diapers also provide useful clues. By five days old, fewer than six wet diapers or fewer than three stools in a day, continued weight loss, trouble staying latched, or little audible swallowing are reasons to contact your baby’s pediatrician promptly. These signs need a feeding and health assessment, regardless of whether a tongue-tie is suspected.
Start with hands-on feeding support from a lactation specialist and keep your baby’s pediatrician informed, particularly if you are concerned about milk intake or weight gain. They can observe a feeding, assess latch and milk transfer, and help identify what needs attention. If restricted tongue or lip movement remains a concern, our team at 303 Pediatric Dentistry can provide an oral evaluation and explain our findings.
Painful breastfeeding can feel discouraging, but you do not have to work out the cause alone. A careful assessment can help your family find the right support while keeping your baby’s feeding and well-being at the center of the decision.

For as low as $39 per month, your child can get all the care they need for a healthy smile with our in-house membership plans. Get all the details, and see how you can save on the care your kiddos need.
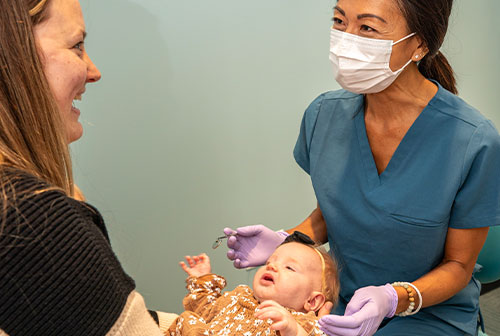
At 303 Pediatric Dentistry, we make life easier with online forms, text/email reminders, and kid-friendly amenities. Wondering what to expect when you bring your child in for their first appointment?

Enjoy a kid-friendly space with ceiling TVs, cozy blankets, headphones, and a fun play area. Parents can relax with a drink while our team provides expert care with advanced technology.